Showing posts with label nursing. Show all posts

Friday, October 26, 2018

RN Staffing Ratios

h/t EDNurseasauras


EDNurseasaurus had a post about MA and staffing ratios, and a very typical shift in any ER in the country.

I may have covered this on this blog before, but it bears repeating:

CA calling.

1) I started in the pre-ratio days.
On but one memorable night in Busiest ER On The Planet (no, really!), I was the third nurse in triage.
My assignment:
Everyone coming in on ambulances too weak/fragile/fall-prone to put in a chair.
Everyone seen, treated, admitted, but not needing a monitored bed, so pulled out so we could hot-stack new patients in their old rooms, and the pre-admitees moved to the hallways.
All the traumas downgraded from trauma monitoring, and in the back hallway.
The fresh chest pains who needed to be moved to the EKG tech booth, then back to the triaged-but-no-bed-open pit.
Move the admits to the floor after calling report, when beds become available: no tech. 18 floors.
Get food/water/urinals/bedpans/blankets/pain meds/barf basins for any and all of the above.
Discharge anyone seen, treated, and released in my flock.
Total body count tonight, just for me: 79.
Seventy. Nine.
I shit you not.

As I received report from day shift, thinking he was kidding me, and then finding out he was serious, I did some napkin math: at 5 minutes apiece for vitals, that's 12 an hour. 6 + hours to get from A to Z, and start with A again.
"Yeah, that sounds about right." he confirms.
He only tells me the highlights on the 10 sickest ones. The other 69 are either unknown, stable, or GOK: God Only Knows.
I look at his vital signs updates. In our 1-2 hour standard-of-care ER, they are listed every q6+ hours.
Spot-on.
In the pre-EMR world, I spend over an hour just finding the charts, locating the bodies that match the charts, and writing down a list of the names on everyone's favorite ER scratch paper, a brown paper hand towel. (*Bookmark this note.)

I locate a portable vital sign machine, and except for full-arrest traumas, it takes the entire staff, including Trauma and ER Chief Attendings, about 3 minutes to realize I have the right of way at all times, owing to my demeanor, size, and attitude, and they'd better GTFO of my path, or be run over like the extra in the chariot race in Ben Hur.


Vital signs - urinal - blanket - pain med - vital signs - jello - straw - blanket - vital signs - bedpan - water - report - transport - vital signs - accucheck - snack - vital signs.
Lather, rinse, repeat, 200X.

Come 7AM, I have six patients left. No one died, everyone got to the floor/a room/discharged/whatever.

Last year, going through my papers, I found the *paper towel, with all 79 names. It went home in my cargo pocket, and I was hoping JCAHO would stop and ask me about the place.

As if. They took one look at the place after 5PM, pronounced "Privacy issues must be challenging for you." and were never seen in the ER again.
2) A few years later, CA (i.e. nurses in CA) put nursing ratios on the ballot. It sailed passed voter acclaim, over the fear-mongering b.s. of penny-pinching corporate sh*tweasels.
For ER:
Normal: 4:1
Critical 2:1
Super-critical trainwreck 1:1
If I have one ICU player, I can have 2 normals as well, for 3 total
And obviously, if TSHTF, and there's a train wreck, plane crash, 7.0 earthquake, you're gonna get what you get, and suck it up.

It's still too much sometimes, but is one helluva lot better than nothing.

And any place busy, you're getting patients shoved up your butt as fast as you D/C the last one, with about 60 seconds to strip and flip the gurney, shpritz it with cootie-cide, and slap a fresh sheet on it.
I've taken up my ICU player, only to return to two fresh untouched normies or another ICU player before I even get back with the empty bed.

That's everywhere, all the time.

Ratios? Hell yeah!
Next stop: mandatory ancillary staff: EMTs/CNAs, etc.
If I and another nurse split a tech, that tech, for 1/4 to 1/3 of my hourly rate, doubles my output and productivity and, can do all the stupid but important stuff you don't need a license to do: vitals, blankets, water, code brown-yellow/ transport to x-ray/CT/U/S, the M/S floor, doing EKGs, D/C'ing IVs on patients for D/C, running samples to the lab, etc.

Paying me $40/hr to spend twenty minutes looking for a fricking tube system transport container to tube my samples to the lab is cost-ineffective b.s., and keeps me from doing patient care. And I spend three hours out of twelve a night doing that. So I point out regularly to manglement that they're paying me $120/shift to play hide-and-seek with $40 worth of plastic, while lawsuits are waiting because I couldn't care for $50K patients. (Whereupon, they look at me as if I've grown another head.)

We could have enough techs to speed throughput for a thirty-something bed ER, for the price of one additional nurse, and there'd only be 1200 ambulance company EMTs who'd leap at a chance for 12 hour shifts instead of 24, benefits, and a chance for tuition reimbursement to become RNs/PAs/MDs, so of course fully staffing techs is not a staffing priority, because they could fix it in about 5 seconds, forever, and have a 100-person float pool to ensure we'd never be short techs, even with 10 psychs needing sitters.

But they'd have to pay money for that, while simultaneously cutting wait times, admit times, and sending patient satisfaction scores to the moon, so, not a priority for the clipboard commandos and the Good Idea Fairies who haven't been at a bedside since the Johnson Administration. (I'm not sure whether it was Lyndon's or Andrew's.)

I feel ya, sister.
MA should vote "Yes". So should the other 48 states.

Thursday, October 25, 2018

Somewhere Else


It's happily rarer than people imagine, even in knife-and-gun-club trauma centers, but Death visits the ER.

Nobody's death comes easy, even the gang-banger who brought a knife to a gun fight, as his mother sobs agonal soul-shaking cries to the heavens. It's not my job to pass judgment, nor torture the living with the final sins of the dead. They'll be able to do that themselves anyways, and for months, soon enough.

I hate death with a passion when early, or some unbidden surprise visitor, and only when the awardee has lived at least their threescore and ten can I see it as a transition, while for only those dying in terminal pain is it the truly welcome arrival of a long wished-for friend.

The sudden, random, unexpected variety is waste beyond explanation, and the recipient of my quiet rage. Like Captain Kirk, I don't believe in the Kobayashi Maru scenario, and the ones you couldn't pull back are the hardest to bear, and the ones you remember long after the others happily fade from memory.

In Gene Hackman's line in Uncommon Valor, some faces never leave your mind's eye, but you make friends with them. Not to do so would drive anyone mad.

This very morning I was happy to be working on a critical patient, because it kept me too busy to deal with the one right next door, dying with no help nor hindrance from me, despite the earnest efforts of 20 others, and I was glad to be able to let others focus on that problem while I got my guy - awake, alert, and very much alive - ready for the cath lab and then ICU. It could have just as easily been the other way around.

I understand and pity the doctors, because they always get to make the notification, generally face-to-face, and they try to keep it simple and as subtle as a scalpel slicing your throat: "Your xxxx is dead. We tried everything we could. I'm very sorry for your loss."
And then understandably try to get back to work on the living, because there are always more live patients to see.

Dealing with the new patients in the room, the next of kin, family, friends, coroner, mortuary, etc., and calling to tell those unknowing to come in, but safely, and without revealing news over the phone, falls back on the nurse responsible for the man or woman or child they'll eventually have to disrobe, clean up, make less fearsome, and remove pads and tape, while leaving tubes and IVs and such in place, in case the coroner takes the case. Covering the patient for modesty, removing blood and worse; and then, after all the sobs are finally spent, zipping them exactly as naked as the day they entered the world into their final sleeping bag for that trip to the Eternal Care Unit. Tag on the toe, tag on the zipper, hands crossed, and please God, in the couple of hours' grace before rigor mortis starts to stiffen limbs and make it impossible to put grandma or auntie or son Jack into the bag without difficulty, and no limbs extended to other points of the compass than due south.

I've bagged some dozens, of all ages. Some mine, some as a favor to an overwhelmed co-worker. Gently and respectfully, sometimes with help, sometimes alone.

Mindful of the fact that fluids accumulate, muscles relax, and fluids follow gravity. Bad enough to handle the dead without getting slimed by them after their departure. Worst of all, the traumas, some where they've cut them open to reach the heart and stimulate it by hand, often to find the offending missile has penetrated the bullseye, and rendered further efforts more than futile, and sometimes after the patient has been sawn virtually in half from each side, with only the spine maintaining the semblance of a whole person.

I don't know what others do, but I tell you freely and honestly, I talk to them as if they were still there as they're being prepped for that last gurney ride. Maybe they still are there, or nearby, in some way known but to God. I have no idea how soon the bus gets there afterwards, or how quick the departure occurs. They may even still be alive inside there, seeing and hearing, trapped inside the body for a minute or few as things fade away after everything fails. It's simple respect for them afterwards, and it helps me to deal with what I'm doing. Quietly, but sincerely, knowing this is as close as I'll ever be to the doorway they've just entered until it's my turn to be zipped into the bag. They get the same compassion they'd merit if they were still breathing, because they're not carcasses.
Not yet.

I'd happily never have done it, but if not me, who? At least I know it'll be done properly, and with what measure of dignity I can accord someone who probably woke that day with no idea it would be their last.

I have my own suspicions as to what happens to them afterwards, but no one truly knows, nor but seldom is in any great hurry to find out, the trip being always a one-way turnstile.

At this point in my life, I still agree with the man who, when asked where he wanted to be when died, answered quite sincerely, "Somewhere else."

Thursday, September 13, 2018

All This, And They Pay Us!


Some time back, on absolutely my second shift ever at Shoestring General.
I'm at the back end, getting the hang of yet another EMR, and doing pretty well with all my patients, but then again even though I'm new here, I have more ER time than everyone else on the shift combined, except the charge nurse.

So things are busy, but steady, except for Baby Huey*.
This particular Not My Patient Tonight is on a 72-hour psych hold, for being off his meds, and playing in traffic. Literally.
Boom: danger to self, on a hold per PD, instantly.
So he's goofy, but not violent, and not all there mentally. with his very own 95# sitter to tend to keeping an eye on him. Which is sort of a disparity right there.

Physically, he could play inside tackle anywhere from Oklahoma U. to the Cleveland Browns. Call it 6'5", and somewhere north of 275#. But he's pretty soft-spoken, and re-directable when he starts to mentally drift. So it's cool.

Until about 0445AM, when he's told for the nineteenth time that he cannot leave, because psych hold, and finally, through the voices in his head, the penny drops.

I'm standing behind the desk at main station when he wanders out into the hallway.

"Baby Huey, you need to stay in your room please" says his sitter. "You have to stay here tonight."

"No, no, no! Gotta go now!" (direct quote) saith Huey. Who then proceeds to take a running start at the lobby door, barefoot, in just a hospital gown.
BOOM!


He hits that thing like Dick Butkus hitting a slow QB, and that door swings through 180° so fast and hard it sounds like a cannon when it hits the outside wall. Thank a merciful god there's no one on the other side, or they'd have been launched like a high pop fly past center field, and generally towards Hawaii in low earth orbit.

Before we can even pursue, the waiting room confuses him, so instead of exiting, he heads down the main corridor to the rest of the hospital, where he encounters a series of locked - we're talking electronically and mechanically - double exit doors.

Slap-slap-slap-slap-slap-BOOM!

Slap-slap-slap-slap-slap-BOOM!

Slap-slap-slap-slap-slap-BOOM!

We're just getting to the lobby, and he's already three doors down, having crashed through them like the opening scene of Get Smart, but at warp speed.


Locked doors? No problem. He's hitting them so hard, the metal jambs are flying loose and taking chunks out of the drywall when the pieces coming off finally land. If any of the 90# Filipina nurses on the floors were walking by, they'd be little crumpled lumps embedded into the opposite wall, but amazingly, he hits no one. Or else they're diving behind counters like the running of the bulls in Pamplona.


We're rounding the corner  just in time to see him blow through three more doors, flying through med/surg, telemetry, and surgical wards, now under a full head of steam, and with his southern exposure flapping in the breeze as the gown parts. He even eats it a couple of times, taking a couple of big faceplant tumbles, but before anyone can complete the tackle, he's back on his feet, legs churning for the end zone. Our slower guys just follow the trail of staff with shell-shocked looks lining the halls after the parade's gone by.

Finally, he runs out of hospital, and he hits an emergency exit in similar fashion, booming through it as well, and bursts out into free oxygen of the pre-dawn air on the backside of the hospital building. And runs smack into a nine foot expanded metal fence he can't climb.

By the time we get to the exit, he's pivoted, found the locked exit gate, and can't figure out the latch, but no matter. Up the fence he goes, using the pushbar as a footing to climb up.

Four of us from the ER, joined by two more guys from the wards he blasted through, are all in hot pursuit, and his momentary vertical attempt allows us to catch up to him. Now we've got him for sure.

Before he can get over, two of us grab his gown, and start to pull him back inside, before he's out on the side streets.

So he shimmies out of the gown, and crashes, now butt naked, the eight feet to the sidewalk outside. We got the empty gown, and he's gotten to the street.

Not being crazy or confused, we open the gate, and hurriedly try to form a loose circle around him.

He takes tumbles, but gets up, and continues to head away from the hospital.
We circle him, but if anyone gets too close, he bolts. We're trying to herd him back towards home base, but he's not having it. Oh, and he's screaming and babbling incoherently as we pass through slumbering suburbia.

It's still dark, and early morning, but people are starting to hit their morning commute on the local streets, and we're trying to keep him (and us) from getting run over.

Cars approach, and we keep one eye on Baby Huey, while waving traffic to go a different way. Seeing six guys in scrubs chasing a huge naked screaming guy down the middle of residential streets at 5AM, they get the hint, and drive away in any other direction.

We keep trying to at least make Huey turn and head into the quiet residential side streets, but like a moth to a flame, he's headed for the bright lights of the main drag, a busy boulevard with morning traffic getting heavier by the minute in the pre-rush hour darkness.

Meanwhile, one of my compadres is keeping the ER advised of our progress on his cell phone, and they're relaying it to the local PD. We hope.

We keep trying to direct the one-man stampede towards safer paths, but he's just not going to go along.

We're about 50 yards from the boulevard, and traffic flying past in clots with each green light, and he looks like he's getting ready to bolt through traffic.

And finally, fortune smiles on us. As Baby Huey is half walking, half-trotting, he gets to a curb next to the corner lot, about twenty feet from multiple passing cars, and then Hallelujah! there's some sprinkler water runoff in the gutter. He hits it barefoot, slips, eats it hard, and he's down!

"Dogpile him! Now!" I yell, and four nurses and two techs all pile on Huey simultaneously, before he can manage to struggle up on his feet again. Everybody gets at least a limb, and I throw my ponderous bulk right on top of him, holding on, and laying there like a big human sandbag to keep him on the ground.

Now it's a stand-off. He can't get up, but we can't get off, or do anything more than throw our body weight on all his limbs. So we're just one big half-naked 14-legged mess on the pavement, looking like six guys at the rodeo, all trying to ride the same bull at the same time.

We dare not turn loose of him for a single moment, or we'll be doing this again somewhere else. If he makes it through traffic, now only a  bare couple of yards away from where we're all playing on the ground.

A couple of early risers and even homeless people at the kwikie mart across the street see the ruckus, and ask if we need help.

"Yes! Call 9-1-1! Now!!!" we shout, holding on to the bull for far longer than the eight seconds in a proper rodeo. We're too busy to do much but maintain the situation.


"This was *not* in the job description!"


Finally, after something between one and five minutes, which feels like an hour, a black-and-white pulls into the intersection across the street. One of us risks letting go with one hand and starts waving frantically. We're rewarded with flashing lights, and the growl of a Dodge Charger coming right towards our melee at full throttle.

A squeal of brakes, and Officer Tackleberry comes flying out and lands on top of the huddle.
It still isn't close to enough, but it helps. A bit.

"Hey, guys. How's it going?" he asks with a big grin.
"We've got to stop meeting like this." I wisecrack right back at him.
We all giggle a bit, and the wrestling match continues.

As Tackleberry calls on his radio for more back-up, we try to get better control of Baby Huey's arms, and start s-l-o-w-l-y moving them to where Ofcr. Tackleberry can get a handcuff on a wrist. It finally gets there, and the first cuff goes on with a satisfying cl-click. But we can't get Baby Huey's other ponderously large arm anywhere near close enough for the second half of that act. But we're still holding him down with all our might, and he's tiring, ever so slightly.

Tackleberry reaches for his second set of handcuffs, just as his sergeant rolls up, and joins the festivities. Finally, we manage to get a cuff on wrist #2, then click the empty cuffs in each set together for the win. While Tackleberry and Sgt. Dooright do cop stuff with the locking mechanisms, we concentrate on keeping Huey from kicking anyone, and keeping his head protected from the pavement, because he's now trying to beat his way through the asphalt, forehead first.

Finally, a fire engine and a paramedic ambulance arrive. They throw a blanket under Huey's head, and it takes six hospital workers, both cops, and four of six firefighters to roll, lift, and place Huey gently on the ambulance gurney, velcro his limbs to it, buckle him in, and lift the whole package up and into the ambulance for the return trip to our ER, several blocks away.

A couple of our guys ride in the ambulance with the paramedic, and everyone who came in a vehicle drives to the ER.

The other four of us hoof it on foot back home, exchanging high fives and fist bumps, amazed that we finally wrangled our wayward guy without anyone getting seriously hurt, including Huey.

We beat the medics and PD to the ER by a couple of minutes, and then do the whole thing in reverse to get him into the ER from the ambulance. Per doctor's orders, we've already got a sedative ready for injection, which is given to Huey on the stretcher.

Once it kicks in, and he's too groggy to resist, it once again takes ten+ people to detach him, lift, and move him to our hospital gurney, and secure him until he's fully out.

And tell the story you just read to those left behind to mind the store, while we were out and about on the Great Crazy Patient Hunt.

Once things calm down, we pull some extra labs on our psych guy. The doc's worried there might be some controlled substances on board, but we also do basic blood chemistry.

The reward is finding out that Baby Huey was probably wandering the streets for days, and not drinking enough water. And no drugs on board, just plain nuts, but he's in pretty severe rhabdomyolisis. Which means his body, without any food to eat, is eating itself, and overloading his kidneys with toxins from muscle breakdown to very near the point of organ failure.

Baby Huey's not just batshit crazy and off his meds; he's very, very sick. We get multiple IVs going and start blasting him with the fluids he hasn't bothered to drink for days. Instead of going to psych placement, he needs to go to ICU that morning. I catch up on all my other patients, and now I inherit care of Huey, who's waiting for the next ICU bed. We squeeze in a full debrief for the night house supervisor, and a multipage multi-person incident report, in between patient care. Huey spends a week in the ICU, calm as a lamb, getting his psych meds every day, along with the meals and water he'd skipped in the tsunami of crazy he was living running around on the streets for days. He gets everything else he needs, until he's medically cleared for a psych hospital to pick up the ball. (They don't do medical problems, and we don't do crazy, so he has to be in great health everywhere but between his ears before they'll take him.)

So in a group effort, police, fire, EMS, the ER, and ICU save his life so he can come back to planet earth.

He could easily have been hit by a car and injured or killed. He might have caused a crash that hurt additional people. The police, alone, even at 2 or 3 or 5 to 1 on him, wouldn't have been able to taze him or wrangle and wrestle him into submission. They might have ended up killing him given his strength and aggression. It would have made wide news release, and given them a black eye in ripples outward that would have lasted for months. And if we'd just let him go to catch another time, he probably would have had organ failure and died before he was found.

Instead, he was as fixed as we could make him before going to the psych hospital.
On my way out, I passed three guys from building engineering trying to put the Humpty Dumpty broken doors along all the main corridor back into operation.

We thanked the other wards whose people tagged along for the final victory.
I sent a personal letter of thanks to police and fire departments, and made sure they got to senior supervisory levels ("Dear Chief..."), not just a verbal attaboy from a shift supervisor, because they seldom hear the rest of the story, or get thanked by anyone for what they do every day.

They had our backs, and we had theirs, and instead of a tragedy, or multiple tragedies, we all saved a guy's life, and unknown other lives, in what turned into just another wild and funny story from an hour out of way too many years in the ER.

I could hardly wait to see what Night Three was going to be like.
But I'm pretty sure when I went home the next morning they liked my work so far.


*{Not his real name. Or hers. Or xe's. In fact, maybe none of this ever happened, and I just hallucinated it all. Duh. HIPPA, bitchez.}

Tuesday, September 11, 2018

Welcome To My World

h/t IOTW


IOTW links to a story called "Why it’s so hard to get mentally ill Californians into treatment"
(besides the obvious answer, which is because my fellow Californians keep electing them to office):
(EXCREMENTO, CA) For years, Diane Shinstock watched her adult son deteriorate on the streets.  Suffering from severe schizophrenia, he slept under stairwells and bushes, screamed at passersby and was arrested for throwing rocks at cars.Sometimes he refused the housing options he was offered. Sometimes he got kicked out of places for bad behavior.  Shinstock, who lives in Roseville and works on disability issues for the state of California, begged mental health officials to place him under conservatorship—essentially, depriving him of his personal liberty because he was so sick that he couldn’t provide for his most basic personal needs of food, clothing and shelter.
But county officials told her, she said, that under state law, her son could not be conserved; because he chose to live on the streets, he did not fit the criteria for “gravely disabled.”
RTWT.

This is my life, every day for 20 years in the ER, and every other ER, nationwide, especially so if the community is larger than 50K people, and if it doesn't snow there in the winter, multiply that by a factor of 10.

We didn't have 500,000 visits a year at the Busiest ER On The Planet™; we had 1000 regulars who came in 500 times apiece.

I've now been to...fourteen ERs in three counties in nearly twenty years doing this, and it's no different anywhere you go.

Schizophrenia is like heroin addiction: it's a social death sentence, and it's almost never getting any better. The worst part, for family, is that Suzy or John (mostly John, victims are about 1 1/2 times more likely to be male than female) is perfectly normal until late high school or early college, even honors students, and then that last bit of wiring in their heads doesn't go in right. It short-circuits, and they stop being normal, brighter-than-average kids and become, frankly, batshit crazy. I can only imagine the never-ending horror for parents of raising a child, getting them safely past all the normal hurdles of growing up, sending them to college, thinking things are okay, and then watching them completely melt down before your eyes.

Meds help, but only if someone with schizophrenia takes them.
The meds make them feel "weird" (which is what we who aren't schizo call "everyday life" 24/7/365/forever), but they seem fine. So they decide they're not sick, and don't need the meds. And become actually weird, hearing voices who aren't there, seeing people and things that aren't real, and end up in my patch, barking, frothing mad. So we re-medicate them, they get put on a psych hold, they get better, go home, and the cycle repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats. And repeats.

Frequently, after burning all bridges with family, friends, and everyone else, and being thrown out of every care facility in an entire time zone, for cause, they end up on the streets. Where they "self-medicate". I.e., with pot, meth, heroin, benzodiazepines, alcohol, bath salts, paint, glue, or pretty much any substance they can get into their hands, and their bodies.

In a lucid moment, a juvenile patient once confided to me, straight-up, that he got wasted because when he got The Voices In His Head drunk or stoned enough, he couldn't understand them or hear them any more. Pure medical genius, right there.

Oh, and The Voices? They never tell you "You look great!" "Everybody loves you!" "You're a wonderful human being!"

That would be too easy, right?

The Voices always say "You suck. Kill yourself. Everyone hates you. Why don't you die?"

Go watch A Beautiful Mind. Or every scene with Gollum in the LOTR movies. (No points for guessing which sections of those latter movies I will completely skip over, wholesale, in that entire trilogy, because it's too much like pulling a shift at work, except without getting paid.) There was even a great TV MOTW with James Garner as the sane brother, and James Woods as the nut, that they showed in nursing school, because the writers and actors got it so right.

The article tries to pin this mess on Reagan (color me shocked), for signing Lanterman-Petris-Short in CA in 1967. But every other state was doing the exact same thing, and in fact LPS was in the legislative pipeline and conceived under Democrat CA governor Pat Brown, Moonbeam's father, before Reagan was even thinking about politics.

The state - in fact every damned one of them - wanted to get rid of psych hospitals long before One Flew Over The Cuckoo's Nest (which was outdated tripe from 30 years earlier when the film was made, but why let facts interfere with a good screed, right?), simply because crazy people don't pay their bills, you do. So warehousing them in Bedlam was nothing but a money hole the size of the Grand Canyon, nationwide.

And the do-gooders got together with the penny-pinchers, and decided collectively that since psych hospitals were so terrible, understaffed, under-funded, and yet still too expensive, because staff needs salary and crazy people need food and medicine, why not just turn everyone so "unjustly imprisoned for life" out onto the street?
What could possibly go wrong?
"The state budget will save millions!"

Whereas instead, as we all experience daily, they're free to run into traffic, attack people, burglarize and rob and steal to get money for drugs/alcohol/whatever, crap on the streets, and generally validate every reason that we have for why we used to throw a net over them and lock them up for life.

Which we can't do, because you have to be a "danger to self, danger to others, or gravely disabled", the definition for which last means that if you are mentally with it enough to scrounge garbage to eat out of a dumpster, drape yourself in trash bags when it rains, and construct a cardboard pallet and hovel to sleep on and in, you're not "gravely disabled."
Just...eccentric, and living an "alternative lifestyle choice".
Don't believe me, ask the district attorney, the state bar association, and the Do-Gooders League Of America. This ain't a California thing, it's a U.S. of A. thing, coast-to-coast.

So they're free, and now everyone else has to lock their doors, put up bars, keep their kids inside, and pack heat, so that these literal lunatics can run wild and free.

Brilliant.

And the article shows that TPTB haven't figured it out, even after 50 years' time.

The do-gooders just want them to be free (and to hell with their best interests, or anyone else's).
The rent-seekers want more money, and no rules for them.
The families want somebody else to solve (and most importantly, pay for, their batshit crazy uncles, cousins, brothers, and sons).
And the police, the hospitals, and the courts are simply tired of dealing with their bullshit, and that of the interest groups who want it to continue more than they want what we have now to stop.

My bent is a libertarian approach.
After three trips to hospital on a 5150 for being off your meds, we throw a net over you.
We put you in a helicopter, and we drop you off on one of the Channel Islands currently inhabited mainly by goats.
Once a week, the helicopter flies over, and they kick out food bundles.
There are no trees, and the islands are 30-40 miles away, in waters best described as sub-arctic even in July; those people aren't swimming or floating back, ever.
If the family is all broken up over this, they can pay for private care. They can visit them on Shutter Island whenever they like. They can bring them food, clothes, or anything else to make their stay more pleasant. They can even bring doctors and medicine there to address any other needs. The whackjobs are now free to chase butterflies, run around naked, or even try to fly off the cliffs; I don't care.
I don't want them euthanized, or harmed in any way. I want them free. Over there.

What they aren't free to do, is continue to run around in traffic, assault people and each other, crap on your porch, or walk around in society off their meds.
Three strikes, and you're out.
Now they're free, and so are we.

The do-gooders have tried it their way. So have the penny-pinchers.
Now it's time to solve the problem.

Friday, September 7, 2018

Still Alive


Been having too much fun doing other things (including months - yes months - away from the E.D.!) to post here as much lately as formerly, but dropping in, I caught up with the three or four still-active blogs, put one oldie but goodie on life support, and buried three others that were cold, dead, and all shriveled up and dry.

I've also notched two more hospitals on my gunbelt, including a ferocious ghetto trauma center, working on two more hospitals (simultaneously!), and dipping my toes back into getting at least one full-time staff position.
Maybe.

I've mentioned it before, but there's a dearth of worthwhile blogs on nursing, especially for Emergency medicine, and the few worthy ones who pop up once in a blue moon simply almost never last.

I, OTOH, am pretty much terminally incapable of shutting up.
Just been cranking out too much content elsewhere.

So I'll try and put more time into things here, if only because by sheer survival, I'll eventually be the best, oldest, and last ER nursing blog still standing. And pretty much the only one.

As one doc I worked with used to note about the ERs nearby that had closed temporarily due to "patient saturation" (when ours never would, legendarily so), there's only one reason they did that:

"It's because they're weak."

Saturday, December 30, 2017

The Show That Never Ends


So, with the entire hospital full and packed to the rafters this week, X number of E.D. beds, and 4X number of waiting room patients all friggin' night, I walk into my shift after clocking in early, because of the page of a violent patient in the E.D.

Four hard restraints, three assaulted staff members, two police responses, one bite mark, and a cuckoo in a bare room later, and that issue is settled while the meds kick in.

Oh, and no points for guessing who's getting that patient as part of their assignment.
So as the night wears on, Fate has firmly tattooed her heelprints on my backside, because I'm getting my ass thoroughly kicked, and even though we're closed, we get a call we can't turn away, for a STEMI inbound in 5 minutes.

And I'm also doing the critical beds tonight.

FML.

That'll be me in the white tonight.
 

So our patient arrives, with the paramedics having done damn near everything (mad props, guys), he's got a STEMI on the field 12-lead, tombstones on the 3-lead monitor, and a STEMI on our 12-lead. And a classic CP presentation. So we're pretty sure it's a heart attack. We dotted all the "I"s and crossed all the "T"s, and we're just waiting for the cath lab doc's arrival to move him over, when the little stinker patient codes. Fifteen seconds of compressions and one defibrillation later, he's back, with the wife biting her fingers off watching, and off he goes to cath lab, finally.

Where it turns out he's got one coronary artery 99% occluded, and another distal one that's at 90%, both of which they stent.

So as I leave, the family is in the ICU waiting room, and I've already talked to his ICU nurse, where the patient is smiling and joking with the nurses, and liable to get a few more decades with his family, after getting to the hospital just in time.

Because everyone from the paramedics to the E.D. to the cath lab to the ICU are badass rockstars, on their "A" game.
And I get to leave the family with smiles, instead of tears.

That'll be me as I walk to the parking lot that morning end of shift.

Saturday, December 9, 2017

Stream Of Subconciousness


welcome to Hell I'll be your tour guide I love the sound of a waiting room full of screaming babies at the beginning of the shift because at least you know it has to get better everything's done on all your patients but the entire hospital's full so let me make sure everything's really all done oh look, a few details missing hey we're just waiting for beds and waiting for beds and waiting for beds and I don't know how long it's going to take another call light ma'am the alarm goes off because you keep bending your arm and playing with the pulse ox why haven't I sent my patients up maybe because you gave us bed assignments that still have the old patients in them oh hey they moved all their patients out now so all your beds are ready simultaneously but you'll have to transport them all yourself because we have no tech and there's no transport are you ready for report see you in five minutes are you ready for report see you in ten minutes are you ready for report see you in twenty minutes are you ready for report see you in about half an hour tell triage all my beds are empty clean and ready for the next batch ready for your lunch break see ya so we loaded up all your beds but one full arrest found down doing cpr eta five minutes out they're here PEA stop compressions vfib CLEAR we've got a pulse vfib CLEAR PEA resume compressions pulse check vfib CLEAR we've got a pulse get me an ekg right away doc vfib f**K! CLEAR we've got a pulse vfib CLEAR PEA resume compression pulse check we've got a pulse here's the EKG if that pulse holds we can get them to cath lab vfib F**K! CLEAR pulse is holding cath lab is here yes sir you can go with her there's a waiting area the surgeon will come find you right afterwards ICU is still full so cath lab is bringing the patient back here after they're done surprise the cardiac stuff wasn't the reason at all but your patient isn't going to make it and there's nothing else we can do great I'll just tell dad to explain to the four young kids that mommy's never coming home again with only two weeks from Christmas that should really cheer them all up but the chaplain's here Holy Father, we ask you to please ICU is sending a nurse to monitor your patient until something opens up in the unit, so you can just take care of the other patients you have while the twelve family members are sobbing their hearts out across the hall from the crazy patient we just gave you who decided he's fine and wants to elope because he's crazy whatever and hey look the docs ordered food for everyone and thank god it's two hours until day shift and the waiting room is finally empty and now I only have twelve patients in that room and the one the ICU nurse is taking care of is the only one in there with nothing to worry about if I hear one more heart-wrenching sob I'm going to completely lose it myself and then I'm no good to anyone and why isn't it shift change yet my knees were over tonight five hours ago free at last free at last and how come the shittiest nights ever in recorded history are always the first of three in a row instead of the last one, every single time, forever and Dear God, WHY? WHY? Just WHY...? hug your kids and WTH? how am I ever going to see to drive home when it's so damned dusty inside my eyeballs

So, how was your night?


Some days, I actually get home with enough energy to go do a couple of miles of jogging, have a nice shower, and go to bed.
Other nights, I get home with enough energy for a short bike ride, then have a shower, and go to bed.
And then, thank a merciful heaven not too damned often, are days like today: when I'm putting on the gloves, and beating on the heavy bag until my arms are too numb to hold up, and my soul stops hurting, so I can stumble to sleep from exhaustion, and hope I don't wake up until it's time to get up again for the next shift.


Monday, November 20, 2017

Level I Drama Center


There are precious few things you can control as a nurse.
As a nurse in the E.D., that number dwindles even more.

Because whatever comes in the front door, or gets delivered on a platter at the ambulance bay, you're getting. 
An entire basketball team of DKA patients, all with blood sugars of over 900, and the highest at 1300.Back to back to back to back STEMIs, all going to cath lab.

Train wreck stroke, who gets an ICU bed, followed by another train wreck stroke.
Four hot appys in a row, the night the whiniest surgeon/OR charge nurse is on call.
Ten psych patients, half before lunch, whom you get placed, followed by five more.

Tag, you're it!

And, truth be told, that can actually be the fun part, when you dig in and get it done, because you get an oak leaf cluster on your Badass Recertification Ribbon.

But there are things you can control.
Write them on your hand in sharpie in case you forget.

1) Don't make your workplace a Level I Drama Center.
I'm working travel and registry, and I promise you, I'm all out of f***ks to give about whatever bitchy little internal squabbles you want to unpack and play with in the middle of a code, or a biblical level of ambulance bay shitstorm.
Do that to me in the middle of a code, and I will wait for you to go into the med room, I will bring a #11 scalpel, and I will cut your carotids, and leave your carcass there for the next luckless sumbitch to find and deal with, I swear to you.
Do it because you have nothing better to do on an average busy night and I'll tie every monitor cable in all your rooms into square knots, I'll triage you every crying puking kid with a fever, and I'll pay the lab tech to tell you all your blood draws were hemolyzed and need to be re-drawn. Better than 50/50 odds they don't like you either, and will do it for free. Ask me how I know.

2) When a co-worker is drowning, you throw lifelines, not boat anchors. 
I'm not talking about the one who's never around when you need help; letting them drown is karma in action. But FFS, when you're caught up, and you see someone else getting beat down, pitch the f*** in. And when somebody does it for you, you say "Thank you", and you owe them a solid, which you pay back the next time it's their turn getting fed into the Giant Woodchipper of Karma, feet-first.
Sometimes just doing one thing for them can take the last straw off the camel's breaking back, and turn their night around. I've been on both ends of that deal, and it's really a thing.
If you don't have that work ethic, you should die of crotch cancer.
Slowly.

3) There's no "Fuck you" in "Team".
If I have to remind you of this, you've already fucked up, and you're not on the team.
I am middle-aged, devious, under-handed, and I have a memory like an elephant, and I will pay you back, with interest, when you've forgotten why you're getting the 30-foot-long party sub sh*t sandwich.
And then I'll make sure you get seconds.

I generally enjoy my job, I appreciate everyone I work with from janitors to surgical chiefs, and I tell them when they're getting it right. It costs me nothing.

But I have passed the point in life where I care if your feelings are hurt because I had to tell you to stop being a wand-waving crap-stirring drama queen, and in fact, if I see it pushes your buttons, I'll make sure to do it in front of God and everybody at the main station, during shift change, and leave you with a big pie-face of fail to wear around as a trophy.

The patients bring enough crap in the door, some of them because they're having a serious problem.

If you aren't getting enough drama in your life without bringing yours to work, quit your hospital job and watch soap operas.
As an old master sergeant explained to me way back in the day,
"You play my game, and I'll play yours. You work with me, and I'll work with you. But if you try to screw with me, I'll screw you over twice as hard, and then again, and again, until you cry for your momma. Do not test me on this."

Wednesday, August 30, 2017

Shameless Product Plug Alert


One of the reasons I love travelling is because I get to see how different places do things.

Today's case in point:
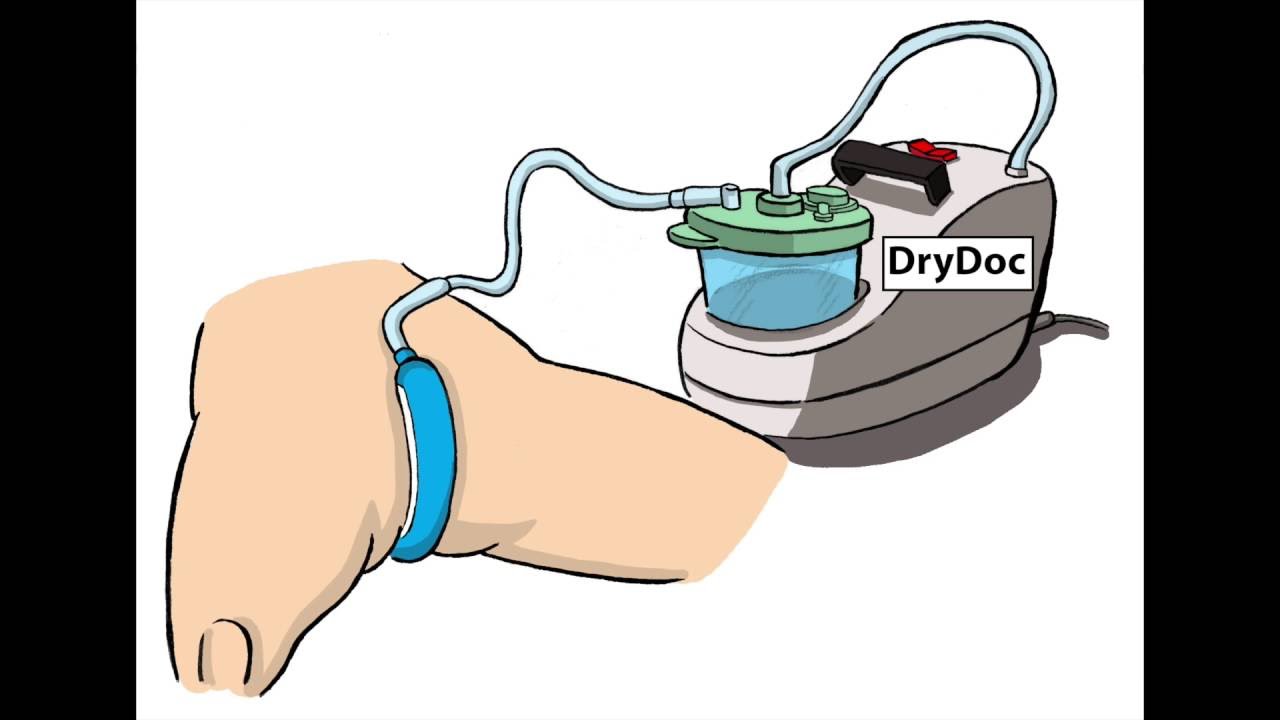
the Purewick External Female Catheter, pictured above.
Which Shoestring General is using (and of which the last umpteen places hadn't yet heard).

In a nutshell:
1) Grandma (or any female patient) is incontinent, or non-ambulatory, a frequent pee-er, or any combination of the three.
2) She's gotta pee, which means sliding a bedpan in under her 400# backside, or broken hip, or moving her bony, cachectic bones, or needs 15 minutes per potty trip to bedside commode or bathroom, twice every hour, or any one of 27 other reasons.
3) Indwelling catheters are on the hospital sh*t list, because they provide UTIs with some regularity, which the hospital now gets to eat the cost for treating.

Enter the Purewick EFC.

As you can see above, it's 10" or so by 1" diameter soft plastic hot dog, with a central wicking tampon-ish core.
You put the white cotton side on your female pt.'s outgoing waste evacuation region, as seen below,
 
inside a diaper or underpants if possible, hook the other end of the magic peesucker to wall (or portable) suction tubing, set it and forget it, and you're done. When it works as advertised (which, anecdotally from me is about 95% of cases), it does exactly what is promised. And even when it's only partially successful it cuts way down on catheters, bedpans, diaper changes, and stinky undies.

It collects the urine in a standard suction canister.
Which can be counted for I+O purposes, sent/withdrawn for standard lab and POCT UA, urine Hcg and drug screens, as necessary. (Urine Cx, not so much).

My no-BS rating: Farking GENIUS! Twenty stars!!!

Eliminates 90% of your female caths as wholly unnecessary.
Which cuts way down on UTIs, and skin breakdown.
And keeps patient and bed less wet and stinky.
Which keeps pt. (and family) happier.

You've just made the day for all CNAs, clinical nurses, risk management, infection control, administration, Press-Ganey, and the CFO, all of whom will wet their pants with joy because 50% of your patients no longer will.

I wish I'd thought of this. I could retire on the royalties.
For that matter, I wish anyone had thought of this 25 years ago, just to save me a few hundred catheterizations. (Plus the ones I missed.)

Seriously, this thing is fantastic. If your hospital isn't using it, clamor for it yesterday, and don't take no for an answer.

Full disclosure: I'm getting zero bucks, nor any other consideration for saying it.
If you're the company marketing it, and you want a testimonial from an experienced clinical practitioner, I'm your pigeon - in return for one steak dinner. Really.
And if you're the Real American Genius who invented it, your steak dinner is on me.
Really.

The first shift you don't have to change 7 diapers, or help tiny frail grandma to the bathroom 10 times, and she can sleep peacefully all night long and stay dry as a bone while you get the ordered UA, and strict I+O tally, you'll want to buy that inventor a steak dinner too.

But if I had invented it, it would have rolled out as the Purewick External Elimination Device, and abbreviated as the P.E.E. Device.
Because I'd totally have gone there.

If your hospital doesn't adopt these, you're living in the 19th century.
Neener neener.


Monday, July 24, 2017

Clipboard Commandos


                                 Almost actual size, but it's not this new and shiny here.

New gig at Shoestring Hospital, in Teeny Weeny ER.

Small, hella-busy, still same old fun.

Except for (wait for it) all the ancillary BS hoops to jump through to start.
Wait, it gets better.

So busy and short-handed, your contract started yesterday. (What's that? You never signed one? Don't worry, we'll get around to that...in a coupla months. Maybe.)
But here's your log-in to complete the same 42 online modules (on my time and nickel, apparently) before you start.
Because the ones you just did for our sister hospital in the same system don't count, because the left hand and the right hand in this fucktarded corporate lash-up don't talk to each other.

How...special.

So, after pounding my head against the monitor for three weeks trying to follow their instructions, it turns out they assigned me no account, so couldn't log-in to the education site, which helpdesk line is so secret, no one in the entire hospital knows it or has ever heard of it, until we reach the threats-of-suspension stage, and it will suddenly leave them exactly as short-staffed as they were before I started, and suddenly shit gets real for them.

Whereupon they "suddenly" discover the secret helpdesk number, and I then find out all the courses they assigned to me in the first place three weeks ago were the wrong ones, and not the ones they've been telling me that I haven't completed, because I couldn't log in, and they never assigned the right ones in the first place.

Because they're all a bunch of chronically and blisteringly incompetent fuckups.

This is my shocked face. I didn't name this place Shoestring Hospital and Teeny Weeny ER for nothing, and Incompetence is one of the core values here.

If I did nursing like they do administration, the dead bodies would be piled up around here like firewood. (And, in all likelihood, they soon will be anyways. But that's another ten stories.)

This will be a short contract. If they ever give me one to sign before I finish it.

And they wonder why they can't find anyone besides brand new grads desperate for a job to become full-time staff? And why they all leave after 366 days?


Wednesday, December 28, 2016

Expecto Patronum


It sucks coming in to the shift after the Christmas weekend, with the ER jammed, and the overflowing lobby looking like the tiger cage at the circus, at feeding time, and the triage nurse feeling like a staked lamb. It's even worse when every time you get a critical patient out of the ER, you get rewarded with another sick patient, even before you get back from passing along the last admit.

It starts getting better when you get everyone out, either discharged home or admitted, and it's really turned the corner when all your beds are empty, and the lobby has been cleaned out too.

Even when it doesn't happen until 6 AM.

Now all you have to do is make that last hour, hoping that nothing will go sidewa

"TWEEEEEEEEEEEEEEE...Medic Six...three minutes out...witnessed full arrest...CPR in progress...intubating..."

Leaving just enough time to clear the decks for action stations and grab the crash cart, because as the one with no patients, guess who's getting the run...?

And everyone shows up, just ahead of The Guy, the purpose of the exercise.
Including the uninvited party crasher.


I really hate that guy.

He tries his best, too. We get a pulse back, lose it, get it back, lose it, get it back, lose it.
The ET tube gets dislodged; the doc re-places it. We go through code drugs like Charlie Sheen at a cocaine lab. Everyone is on their game though. The guy comes in a deathly shade of purple, and we manage to turn him pink and warm with compressions and bagging. Lines go in like clockwork, IV, IO, central line, NG tube, foley cath. A pile of debris and detritus forms around the perimeter of the room, in inverse proportion to how our guy is doing. Apparently you need to fill a garbage bag to save a life, and we're doing our bit in spades on both counts.

Finally, the efforts start paying off, the pulse comes back for good, blood pressure and oxygen sats stabilize, and we start thinning out the garbage piles just ahead of the arrival of the family that last saw their husband/father/brother/uncle being loaded into an ambulance in the dark half an hour ago.

Sometimes, with some patients, the end is a welcome release from terminal pathology, but not this time.

And with an extra little push from timing, a short transport time, and rockstars on arrival, this guy got the A-Team.
And I love it when a plan comes together.


Oh, and f**k you, Death.
Not on my shift.
Not this time.

Thursday, October 13, 2016

Thought For The Day

If you come to the ER and you remember me, you've been here two times.
If you come to the ER and I remember you, you've been here too many times.

Nurses Eat Their Young - Busted


Pretty much calling bullsh*t on that one.

Do all of us, as nurses, run into people that try to pee on our heads and make life hell?
Hell yes!
Do some nurses wimp out and quit?
Probably.
Does that mean everyone everywhere is there to jump you into the gang?
Hell no!

How do I know this? Because when I started out, it was at a great teaching hospital, unfortunately cursed with some of the most godawful bitter rotten bitches and bastards on the planet, stewing in their own little toxic cesspool. I got tough, and then I got out. And having seen it once, I can spot it in about 0.2 seconds, and don't put up with it.

Everybody, in every job or experience, has probably been hazed a bit (mostly in good fun, and just as a momentary prank). Some people get it far harsher, because you're working with a bunch of bitter, twisted douchenozzles. If your work environment is pissing you off after a month, it's Option B, every time, whether you're new, or you've been doing this for years. If so, GTFO.

I bring this up, because I'm currently somewhere they have a constant stream of new staff, between registry, travelers, new grads, residents, etc. ad infinitum. That was true at the first place I broke in too. What's different is that here, what's missing are the bitter old hags who think they were beknighted by Florence Nightengale personally (and honestly, some of them were old enough to credibly make that claim, but I digress), and they're metaphysically certain that their feces produces no odor. The only reason they wished nursing caps would come back was so that they could wear a tiara to work.

There's none of that here, nor most places. In fact, there's seldom more than a couple of nurses who try it nowadays, and they're usually the petty supervisors who substitute attitude for actual bedside skills. The ones who should retire, to save their own lives, and their patients'.

The reason it doesn't thrive so much anymore is that everyone knows we need the fresh blood, because we need the help period, and secondly, the days of the supervisor who can't help at the bedside are blissfully numbered as I speak. Anybody still pulling their weight knows that can't-hack-it supervisors are dead weight, and that includes their bosses, and their administrators. And much like the military, a constant stream of non-returning new hires points rather inevitably to crappy leaders and preceptors, and that metric comes up at annual raise and retention bonus time, in a big way.

Here, I'm seeing experienced nurses precept the hell out of new grads, and getting double-checked on it, so that once the training wheels are off, the new grads cruise, instead of crash. Better for them, better for us, better for patients, better for the hospital, better for the hospital's bottom line.

If you're one of the perennially bitchy nurses that can't stand new grads, don't let the door hit you in the ass on your way to retirement. In fact, why wait? Quit right now, and save even more lives than if you stayed. And if you're a new nurse, feeling like a cat toy for the experienced nurses, you either need to change you profession, or even more likely, change your work address. The nursing shortage is going nowhere, and all you'll get for trying a greener pasture somewhere else is a better night's sleep, and lower blood pressure. And the Queen Snottypants nurses at Jacked Up Hospital will be stuck where they were without you, doing the work themselves, because they suck.

Anybody can have a rough shift.
If you're having a rough trimester, on the other hand, either do some serious soul-searching, or update your resume, and start web-surfing.
Don't be afraid to ask for help, but if it isn't forthcoming when you ask, start making plans to bloom elsewhere. There are no reward points for being a workplace martyr.
You may be a victim, but you don't have to be a volunteer.

Monday, October 3, 2016

Car 54, Where Are You?


Drunk is not a medical emergency.

Note I am not referring to drug ODs, nor to intoxication to the point of cessation of breathing.
It is solely in reference to plain old intoxication. Something which used to occasion a visit to the local constabulary's drunk tank. Which, long and short of it, is where the problem reared its ugly head.

Because, gentle reader, despite a multiplicity of job skills, police officers, sheriff's deputies, and whatnot are many things, and jacks of a host of trades. But "licensed medical practitioner" is not any of them (and I'm okay with that, and about to tell you why).

Y'see, back in the day, Ofcrs. Reed and Malloy used to load drunks in the back of the squad car, and tote them to the drunk tank. Which was fine for drunks. The problem arose because people with head injuries after car crashes, and people having strokes, and people with diabetic-induced blood sugars of 20 all look exactly like drunks when apprehended. But unlike garden variety drunkaholics, they unhelpfully tend to die a lot overnight when placed in a large drunk tank holding cell. This causes consternation for the officers, annoyance for their families, runaway profits for said families' personal injury attorneys, and great aggravation and heartburn at the offices of the legally responsible municipalities concerned.

So the word has gone out, from city council to city attorney to chief of police to watch commander to desk sergeant to every Ofcr. Reed and Malloy and Deputy Fife:

Take all drunks to the E.R.

And I get that, boys and girls, I truly do. You don't have a CT scanner in your car, nor any medical training but the barest state minimums, so to preclude killing people by mistake, you bring them to those of us qualified to tell a drunk from a guy who took too much insulin and not enough dinner before he plowed into 3 cars and staggered into your arms.

Well and good it is, dulce et decorum.

But where all of you ministers of street justice screw the pooch, is that once you leave the few medical emergencies, and the overwhelming vastness of public wastrels, in our hands, or handed off to us by way of the local fire guys, whom you also had to wake up and drag into this mess, is that you, having happily washed your hands legally of them, don't return and take them to jail, nor even issue a summons for public intoxication, once it's medically certain they're simply drunken @$$holes in desperate need of a stay in the Greybar Motel.

Let me make it clear, lest I put it too mildly, that in every ED I've worked in, and on every night of every year of this century, that amounts to between 2 and 20 m*****f*****s every shift, in perpetuity. I'm sure you don't miss dealing with them, having happily palmed their vomiting, urinating, diarrhea, abusive and obnoxious behavior, and even their assaultive escapades, onto mainly a bunch of overworked nurses, techs, and doctors in scrubs. I'm sure your desk sergeants and watch commanders think that's a splendid thing. I'm sure your city minders don't miss the wrongful death lawsuits. And I know for goddamned certain (ask me how, I triple dog dare you) that the sonofabitches in the city attorney's office have never criminally prosecuted so much as one intoxicated drunk for any of the literal dozens to hundreds of techs, nurses, or doctors that are assaulted and battered daily and nightly in any place hereabouts, just like they don't statewide, or probably in any state.

And as another monumental douchebag opined in a similar vein, "What difference, at this point, does it make?"

Well Sparky, it means that sooner or later, you or yours is going to come in the door with your wife, or kid, or parent, having a heart attack or stroke (or, if God is just, it'll be you yourself, and better yet, your chief), and I'll just be too busy to get to you right away, because I and ten or twelve of my colleagues, without bulletproof vests, batons, tasers, or pepper spray, are doing the wild hog rodeo with some out-of-control 300-visit-a-year @$$hole that should have been doing six months in county for multiple arrests for intoxication that you never bothered to make, because policy; or because the loss of $500K per offender, year in and year out for this happy horseshit caused staff members to burn out and leave, and budget cuts due to those ongoing financial losses have left filling the job impossible.

And then your kid, your wife, your parent, or you, are going to sit in the waiting room, and maybe even die. Sucks to be you on that day, huh?

Or, long before it gets to that point, some one of you with two wits to rub together, could be proactive, and start taking the repeat offenders off the menu, and let some judge set them to filling potholes in the summer, and shoveling snow in the winter, for six months at a stretch, and while we might see them once in six months, after a couple such bed-and-breakfast arrangements with the county, either they'd decide on another life trajectory, or we'd have the best-maintained roads in decades.

Maybe think about that the next time you're sure we'll have time for you when you crash your unit, or take a bullet fighting crime. It'd be a real shame to find out the last bed in the ED was filled by Roscoe the Sterno Bum, for the 200th time this year so far, a half an hour before you rolled in on a stretcher, wouldn't it?

Think it over, and do the right thing.